
CardioSeq
Caring for your heart also begins with your genes.
NeoScreen's CardioSeq combines whole genome sequencing with analysis of more than 500 cardiovascular genes, polygenic risk scores and pharmacogenetic information. An integrated genomic approach that connects personal and family history with focused cardiac care.

Exploring the heart through different layers of analysis
Investigating inherited cardiovascular conditions.
The cumulative effect of many common genetic variants.
Genetic information relevant to specific medicines.
Findings are interpreted with the treating cardiologist. Genetic predisposition is considered alongside other cardiovascular risk factors.
Three complementary perspectives on cardiovascular health
CardioSeq examines genetic information at different levels. It looks for variants in genes associated with inherited conditions, estimates the cumulative effect of many common variants and assesses genetic factors that may influence responses to specific medicines. Its value lies in interpreting these findings together, in line with the clinical picture and the referring clinician's question.

Inherited background
investigating a genetic cause and risk within the family.
Polygenic predisposition
additional information for risk stratification.
Pharmacogenetics
information to support discussion of the treatment strategy with the clinician.
Connecting genetic information with cardiology
Which conditions and factors are assessed?
The analysis covers key categories of inherited cardiovascular conditions. The selection and significance of findings are tailored to the history, diagnosis or clinical suspicion that prompted testing.
Cardiomyopathies
hypertrophic cardiomyopathy (HCM) and dilated cardiomyopathy (DCM).
Inherited arrhythmias
long QT syndrome (LQTS), Brugada syndrome and catecholaminergic polymorphic ventricular tachycardia (CPVT).
Arterial disorders and syndromes that may be associated with sudden cardiac death.
Familial hypercholesterolaemia
investigation of genes such as LDLR, APOB and PCSK9.
Metabolic predisposition
genetic markers related to cholesterol, triglycerides, glucose and inflammation, with examples including LPL, TCF7L2 and CRP.
Who may benefit?
Genomic assessment is particularly useful when there is clinical suspicion of an inherited cardiac condition or a relevant family history. Referral begins with a discussion of the history and available cardiac investigations, so that the result addresses a clear question.

People with cardiomyopathy, heart rhythm disorders or another suspected inherited cardiovascular condition.
Families with a history of sudden death or a known genetic heart condition.
People with suspected familial hypercholesterolaemia.
People undergoing preventive assessment in a higher-risk setting.
Athletes with a relevant history or clinical indication, as part of their cardiac assessment.
WGS: broad genomic information, focused interpretation
Whole Genome Sequencing provides information across the entire genome. In CardioSeq, clinical analysis focuses on more than 500 genes associated with cardiovascular conditions. The figure 30× describes mean sequencing depth and is not a diagnostic success rate.
The final conclusion comes from assessing the variant and its relevance to the individual. Family history, age at onset, the nature of the cardiac condition and previous investigations help the team identify findings of clinical significance.
Sources & evidence ↓PRS: the contribution of many small genetic effects
Polygenic risk scores combine the effects of many genetic variants. The programme includes polygenic assessment for coronary artery disease, heart failure and arrhythmias.
A PRS describes genetic predisposition and must be considered alongside age, blood pressure, lipids, lifestyle and family history. A higher score does not mean disease is certain, and a lower score does not exclude a cardiovascular condition. Interpretation depends on the specific model and reference population.
Sources & evidence ↓Pharmacogenetics: more information to support treatment
The pharmacogenetic component examines genes involved in drug metabolism and drug targets, with examples including CYP2C19, CYP2D6, SLCO1B1 and VKORC1. The data can provide information relevant to certain statins, antiplatelet medicines, anticoagulants and antiarrhythmics.

The treating clinician considers the finding in relation to the particular medicine, other treatments and the clinical situation. Changes to treatment or dosage are made with medical guidance; genetic information forms part of the treatment decision.
From a genetic finding to a treatment discussion
Genetic differences relevant to medicines.
Metabolism, response or adverse effects.
Discussion with the treating clinician, alongside the other available information.
From sample to clinical report
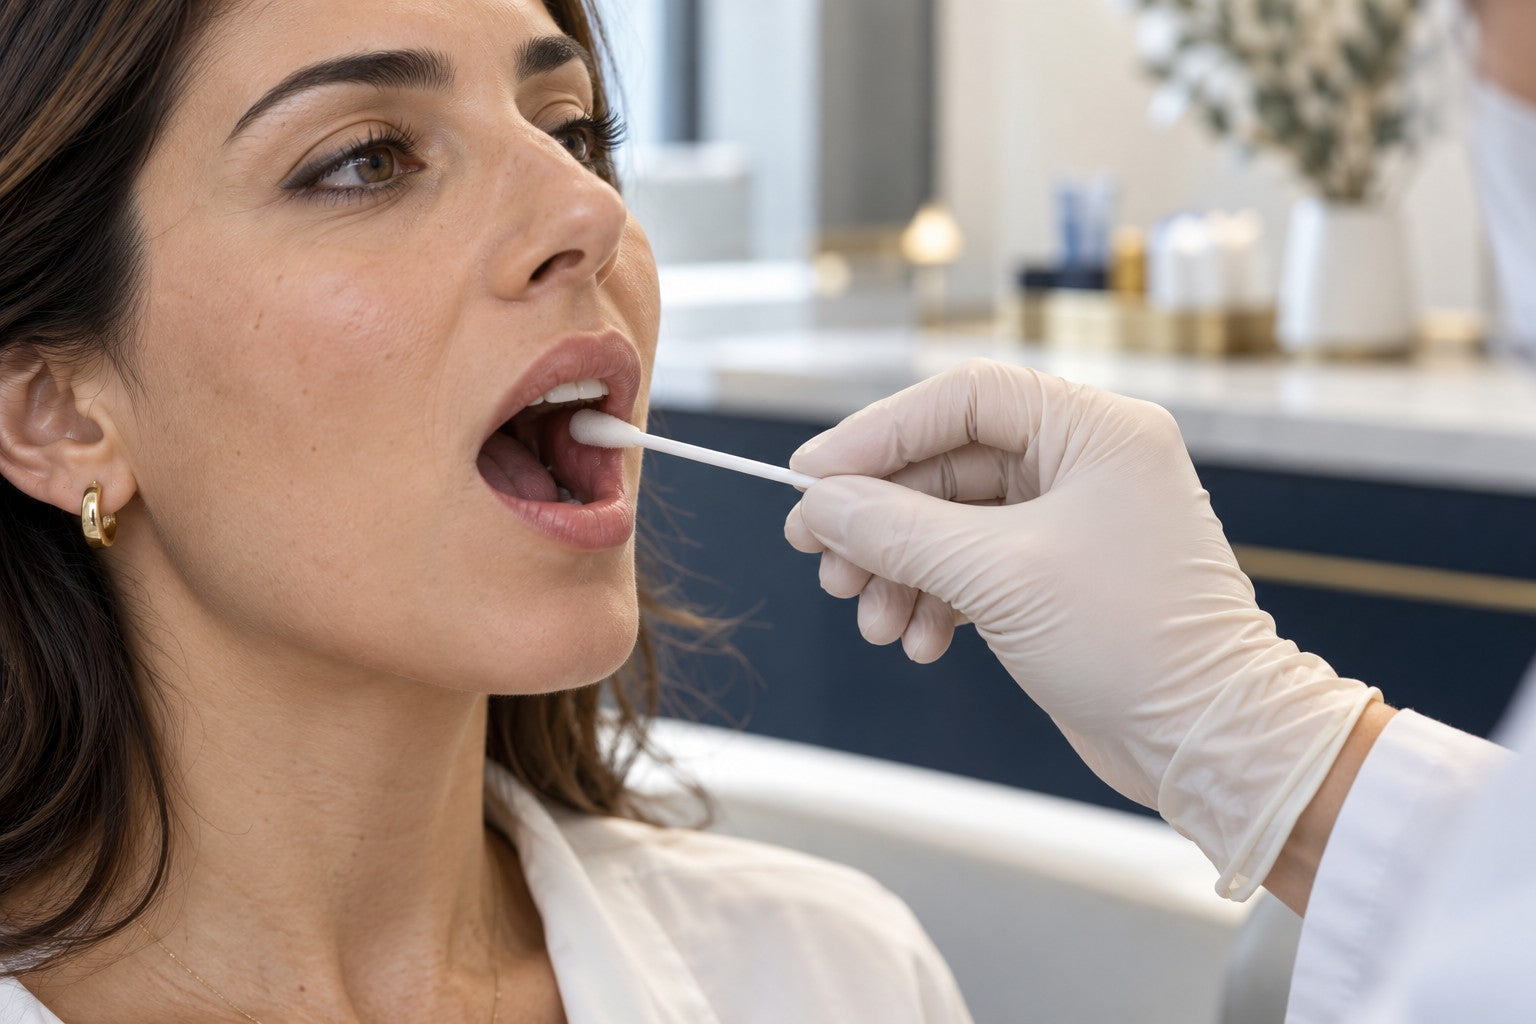
The procedure is organised around the clinical question and concludes with interpretation of the results. The information brochure specifies a simple buccal swab and an indicative turnaround time of 4–5 weeks. Sample collection instructions and turnaround time are confirmed when the test is ordered.
1. Recording the personal and family cardiac history.
2. Collecting a sample according to laboratory instructions.
3. WGS and analysis of the relevant genes, PRS and pharmacogenetic information.
4. Clinical interpretation and reporting of findings.
5. Discussion with the treating clinician about monitoring and, where indicated, assessment of relatives.
How is the result interpreted?
A pathogenic or likely pathogenic finding is assessed in relation to the condition and clinical presentation. It may help investigate the underlying cause and plan family testing. A variant of uncertain significance requires careful interpretation and may need future reassessment.
If no relevant finding is identified, the cardiologist considers the result alongside the other investigations. Cardiac follow-up is based on the overall picture, because a negative genetic test does not exclude every inherited or acquired cardiovascular condition.
Sources & evidence ↓Frequently asked questions
Does CardioSeq replace a cardiac assessment?
Genomic information complements the clinical examination and the cardiologist's findings. An electrocardiogram, imaging and other investigations are selected according to the individual's needs.
Is a blood sample needed?
The CardioSeq brochure specifies collection with a buccal swab. The NeoScreen team provides instructions on the appropriate sample and its transport.
Can it also help my family?
When a clinically significant inherited finding is identified, the clinician and genetics team assess whether targeted testing of relatives and specific monitoring are appropriate.
Does a high PRS mean I will have a cardiac event?
No. It is an estimate of genetic predisposition. Personal risk also depends on other factors and is assessed alongside the medical history.
Sources & scientific evidence
Service description: NeoScreen information brochure, October 2026 edition, p. 8. Additional information: detailed CardioSeq brochure, 2026.
Knowledge becomes care.NeoScreen · 5,000+ WGS / WES analyses
Scientific Director: Ioannis L. Loukas, Professor, National and Kapodistrian University of Athens
Connect genetic knowledge with heart care.
Contact NeoScreen to discuss CardioSeq and the information needed for assessment.
